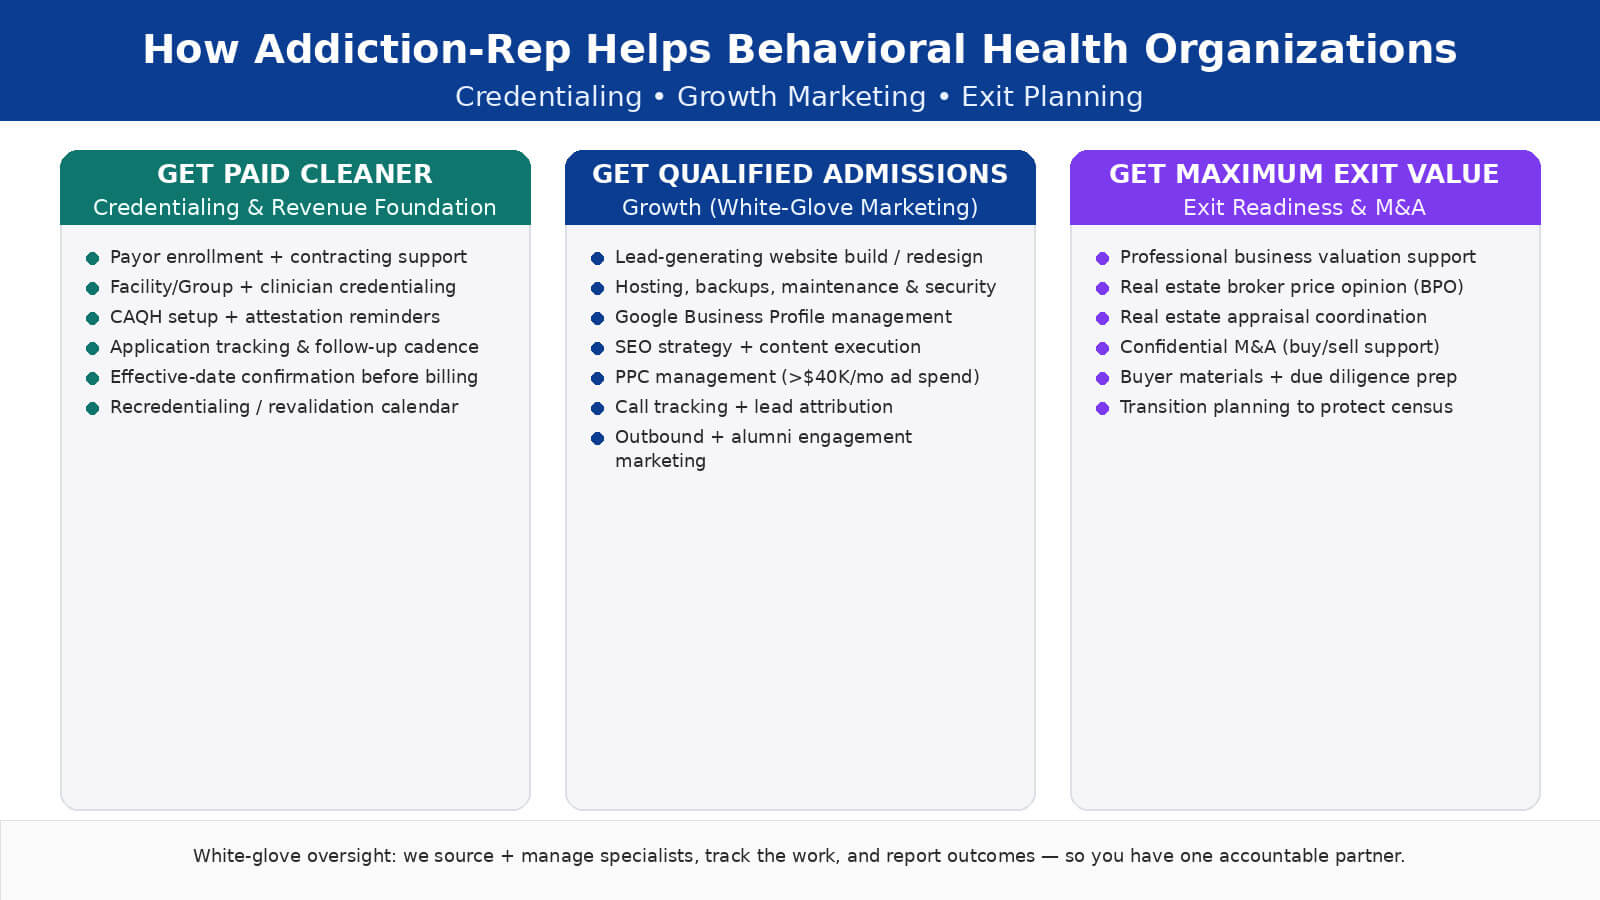
Behavioral health credentialing services by Addition-Rep come in three phases:
Phase 1 — Revenue Foundation (Credentialing)
Goal: Get paid clean + reduce denials
Deliverables:
- org + clinician credentialing setup
- CAQH + rosters + enrollment tracking
- effective-date verification before billing
- recredentialing calendar
Phase 2 — Growth Engine (Admissions + Marketing)
Goal: Get qualified calls you can convert
Deliverables:
- website + hosting/maintenance
- call tracking + attribution
- Google Business Profile + SEO
- PPC (with your minimum spend qualifier)
- outbound + alumni engagement
Phase 3 — Exit Readiness (Value + Transaction)
Goal: maximize enterprise value + reduce deal friction
Deliverables:
- valuation support + story
- real estate BPO/appraisal coordination
- M&A support (buy/sell)
- data room + due diligence prep
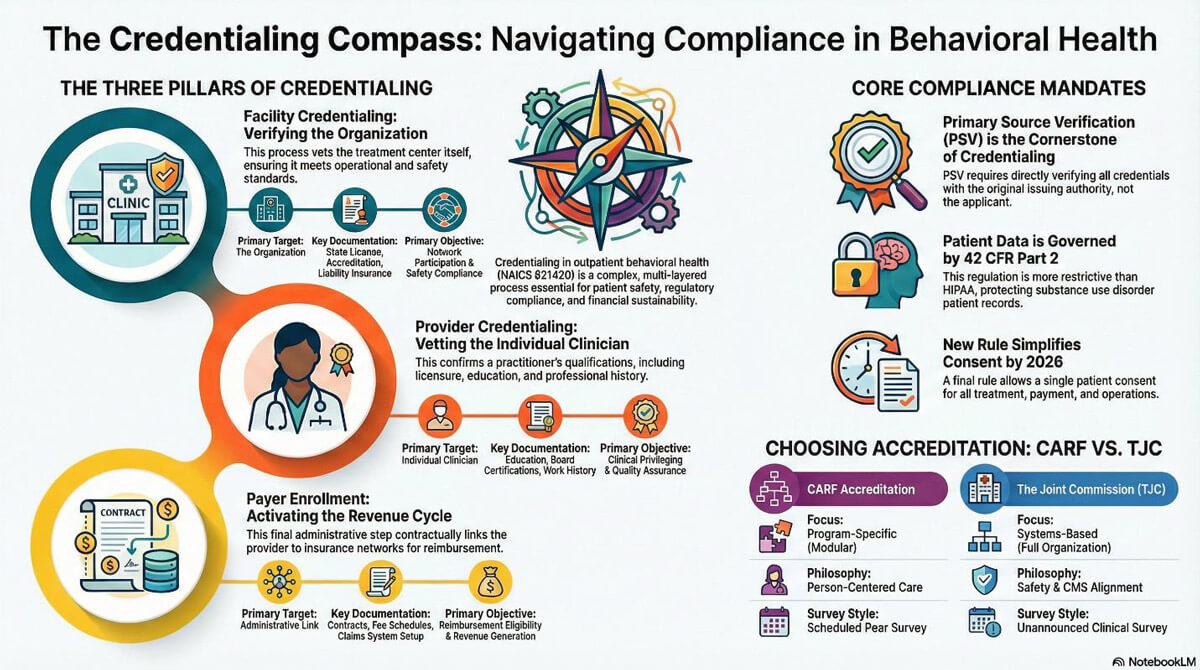
Credentialing in Behavioral Health: Best Practices for Faster Network Participation and Cleaner Reimbursement
(NAICS 621420 | Outpatient Mental Health & Substance Use Treatment)
Credentialing is one of the most important (and often most misunderstood) steps in building a successful behavioral health or addiction treatment organization. It impacts your ability to bill insurance, get paid on time, stay compliant, and grow sustainably.
Whether you’re launching a new outpatient program, expanding to new payors, or adding clinicians, strong credentialing practices protect your revenue cycle and reduce denials.
This guide outlines the best practices for credentialing in behavioral health—designed for substance use and mental health providers operating under NAICS Code 621420.
What Is Credentialing in Behavioral Health?
Credentialing is the process of verifying that a provider (individual clinician or facility) meets the qualifications and standards required by insurance payors and regulatory bodies.
Credentialing generally includes:
- License verification
- Education and training validation
- Work history and malpractice review
- Background checks (as required)
- Sanctions and exclusion screenings
- Insurance enrollment and contracting steps
Credentialing is not the same as contracting.
Credentialing verifies you qualify. Contracting sets your rates and terms.
Why Credentialing Matters So Much in Addiction Treatment
Credentialing affects:
1) Your Ability to Bill and Get Paid
If credentialing isn’t active, claims may deny as:
- “Provider not enrolled”
- “Provider not credentialed”
- “Out of network”
- “Rendering provider not recognized”
2) Patient Access
Many clients won’t begin care until insurance is accepted—or will drop out if billing becomes confusing.
3) Compliance and Risk
Credentialing protects your program from:
- billing fraud exposure
- misrepresentation issues
- payor audits
- improper provider supervision claims
4) Long-Term Growth
Credentialing is often the difference between:
- stable census + predictable revenue
vs.
- constant cash-flow emergencies
Credentialing Types in Behavioral Health (Know the Difference)
Most organizations need credentialing in two categories:
A) Facility / Organization Credentialing
Examples:
- outpatient clinic
- PHP/IOP program
- group practice
- behavioral health agency
Often includes:
- Tax ID (EIN) enrollment
- facility license (if required)
- accreditation documents (CARF / Joint Commission, if applicable)
- NPI Type 2 (organizational NPI)
B) Individual Clinician Credentialing
Examples:
- LPC, LCSW, LMFT
- psychologist
- psychiatrist / PMHNP
- SUD counselors (varies by payor/state)
Often includes:
- NPI Type 1
- CAQH profile
- license verification
- malpractice insurance
Best practice: Credential both the organization and rendering providers correctly—otherwise claims will still deny.
Best Practices: Credentialing Done the Right Way
1) Build a Credentialing “Master File” for Every Provider
Create a standardized checklist and keep all documents in one place.
Recommended items:
- Driver’s license (if required)
- Professional license(s)
- DEA certificate (if applicable)
- Board certification (if applicable)
- Malpractice insurance face sheet
- CV (current, with month/year timeline)
- W-9
- CAQH ID + login details
- NPI confirmation
- SSN (securely stored)
- Practice locations + service addresses
Pro tip: Most delays come from missing documents or inconsistent addresses.
2) Keep Address and Taxonomy Data Consistent Everywhere
Credentialing errors often happen because payor systems don’t match:
- Legal business name
- DBA name
- Billing address
- Service location address
- Pay-to address
- Tax ID (EIN)
- NPI Type 1 and Type 2
- Taxonomy codes
Best practice: Use one standardized “payor enrollment sheet” and don’t improvise.
3) Use CAQH Correctly (and Update It Monthly)
CAQH is required by many commercial payors and is a common bottleneck.
Best practices:
- Complete every section fully
- Upload all supporting docs
- Ensure the provider “attests”
- Re-attest when prompted
- Confirm payors are authorized to access the profile
Credentialing tip: CAQH being “complete” is not the same as being “attested and shareable.”
4) Credential the Right People First (Revenue-First Strategy)
Don’t credential randomly—credential in the order that protects cash flow.
Recommended order:
- Medical Director / Prescriber (if applicable)
- Lead therapist(s) with highest schedule volume
- Group therapy clinicians
- New hires / part-time providers
Why it matters: If your high-volume clinicians aren’t credentialed, you’ll either delay treatment or lose revenue.
5) Start Credentialing Early—Before Opening Day
Credentialing timelines can be long.
General expectations:
- Commercial payors: 60–150+ days
- Medicaid (varies): 45–120+ days
- Medicare (if applicable): often 60–90+ days
- Single-case agreements: 1–4 weeks (sometimes faster)
Best practice: Start credentialing 90–120 days before launch, minimum.
6) Track Every Application Like a Project Manager
Credentialing requires persistence.
Use a tracker with:
- payor name
- provider name
- date submitted
- portal used / reference number
- follow-up dates
- status notes
- effective date
- revalidation date
- contract status + fee schedule status
Best practice: Follow up every 7–14 days until active.
7) Confirm Effective Dates in Writing (Don’t Assume)
Payors may approve credentialing but delay network activation.
Always confirm:
- provider is “in-network”
- effective date is active
- claims can be submitted today
- correct billing NPI/TIN combination is loaded
- rendering provider is linked to the group
Pro tip: Ask payors to confirm effective dates by secure message, portal update, or email (where allowed).
8) Understand Group vs. Individual Enrollment Rules
Behavioral health billing commonly fails due to enrollment structure issues.
Common claim configurations:
- Group bills (Type 2 NPI + EIN)
- Clinician renders (Type 1 NPI)
- Place of service and taxonomy must match payor setup
If the payor requires “individual-only” billing and you submit under the group (or vice versa), claims may deny even if you’re credentialed.
9) Avoid Credentialing Gaps When Hiring or Terminating Staff
Every staff change affects your payor compliance.
Best practices:
- Start credentialing immediately upon offer acceptance
- Do not schedule insured clients until credentialing is confirmed (unless you have a compliant out-of-network plan)
- Remove terminated providers from rosters and payors
- Update CAQH addresses and practice affiliations quickly
10) Recredentialing and Revalidation: Put It on a Calendar
Credentialing is not “one and done.”
Most payors require recredentialing every 2–3 years.
Best practice:
- track recredentialing deadlines
- set reminders 120 days prior
- maintain continuous malpractice coverage
- keep licenses current
- re-attest CAQH regularly
Common Credentialing Mistakes (and How to Prevent Them)
Mistake #1: Confusing Credentialing with Contracting
Fix: Treat them as separate workflows with separate deadlines.
Mistake #2: Submitting With Inconsistent Addresses
Fix: Standardize addresses and use a payor enrollment sheet.
Mistake #3: Missing Supervisory Rules for SUD Staff
Some payors require specific credentials for reimbursement.
Fix: Confirm which licenses/certifications are payable under each payor contract.
Mistake #4: Billing Under the Wrong NPI
Fix: Confirm if payor wants:
- individual NPI only
- group NPI + rendering NPI
- facility enrollment vs. professional enrollment
Mistake #5: Not Confirming the Effective Date
Fix: Always verify active participation before billing.
Credentialing Checklist (Quick Reference)
For the Organization
- EIN / W-9
- NPI Type 2
- Taxonomy codes
- Practice locations
- Ownership disclosures (if required)
- Liability insurance (if required)
- Accreditation documents (if applicable)
- Banking info for ERA/EFT
For Each Clinician
- NPI Type 1
- License(s)
- Malpractice insurance
- CAQH complete + attested
- Work history / CV
- DEA (if applicable)
- Supervisory agreements (if applicable)
Payer-Specific Credentialing Guides
Once you understand the credentialing process at a high level, the next step is mastering the specifics for each commercial payer. The application windows, required documentation, site visit triggers, and timelines differ meaningfully between Aetna, Cigna, and the other major networks. Our payer-specific guides walk treatment center operators through each one:
Final Thoughts: Credentialing Is Revenue Cycle Protection
Credentialing is one of the highest ROI administrative functions in behavioral health. It directly impacts:
- admissions growth
- claim acceptance rates
- cash flow stability
- audit readiness
- long-term payor relationships
When done correctly, credentialing becomes a predictable system—not a crisis.
If you treat it like a compliance requirement and a revenue strategy, your practice will grow faster and get paid cleaner.
Want Help Credentialing Your Program?
If you’re opening a new outpatient program, adding payors, or trying to fix claim denials tied to enrollment issues, Addiction-Rep can help streamline credentialing and payor setup so you can focus on clinical care.
Visit: www.addiction-rep.com
Category: Credentialing • Billing • Insurance • Revenue Cycle Support

